StatCounter

Friday, August 04, 2006

Primary Care is Where It's At

I found yet another article about a micropractice, this one in Rhode Island, which serves as a rebuttal to some recent opinions that primary care is dead.
Ho has no receptionist or other staff members, so immediately after greeting a patient, the two enter into a conversation about the patient's health, a physical examination, and discussion of next steps. The relatively small size of Ho's practice allows her to spend a relatively large amount of time with each patient: at least an hour for a first visit and a half hour or "as long as it takes" for subsequent visits.

As the visit draws to a close, the doctor handles all of the administrative details, including billing and scheduling the next appointment, herself. The results of focusing so much on her patients are clear: although Ho estimates that she's forced to spend more than 60% of her time on administrative tasks, she has over 600 patients, and will soon have to close her practice to new patients that are not family members of existing patients.

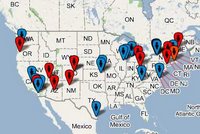
Dr. Ho is on the Map. I suspect there are a lot more micropractices out there than anyone thinks. Hopefully we'll start reading more about them as the word gets out.

Thursday, August 03, 2006

More Micropractices


It's always a pleasure to hear about other physicians who are choosing to go smaller and return to a simpler way of practicing medicine via micropractices. For one thing, it gives me hope that the American medical system can be transformed/reformed into something that makes some sense. For another, it makes me feel like I'm not the only crazy one for trying it.

Here is a recent article from the Santa Cruz Sentinel about someone else who took the leap:
SANTA CRUZ - There's something different about the office of Dr. Maria Greaves.

Sure, there's a tastefully furnished waiting room with a burgundy leather sofa and a toy box. But there's no receptionist, no nurse, no insurance paperwork to fill out.

"I'm everything," said Greaves with a smile.

She is the first physician in Santa Cruz County to adopt a new style of medical practice pioneered by Dr. Gordon Moore in Rochester, N.Y., five years ago.

Here is another article about 2 doctors from Oregon who also decided smaller is better:
Quillin is part of a growing national trend of physicians breaking away from high-volume practices characterized by short office visits.

Tired of seeing more than 20 patients a day and staying on top of the well-being of 2,500 people every year, they are paring down their practices to a few hundred patients, who get a lot more of their time.

Smaller practices can come in different forms. Some are completely solo like Dr. Greaves and myself. Others look like a traditional practice with a medical assistant and nurse. I accept 3rd party insurance like most practices. Dr. Quillen charges a $400 annual enrollment fee plus $75 per additional family member. You can be full-time, or part-time, like Dr. Wible:
Wible worked in several clinics in Eugene and in Washington state before opening her own part-time practice in April.

Her biggest complaint about working in established clinics was similar to Quillin's: not enough face time with patients.
"I like to talk and my patients like to talk. They want to get to know me, and I want to get to know them. You can't do that in 15 minutes," she said.

When she decided to go solo, she conducted several community meetings that attracted about 100 people. She asked them what they wanted from their primary care physician and three consistent themes emerged.

People wanted more time with their doctors. They wanted to be listened to and they wanted to play a role in their own health care.

Wible knew she wanted more time with her patients, the opportunity to help transform the health care system, and more personal time to explore other activities.

To get there, she stripped down the overhead. She employs no one, and does all the accounting and business work in her home office. She sees clients three days a week in an office she rents at the Tamarack Wellness Center in south Eugene.

Because she carries no debt and lives simply, Wible says she doesn't need the typical physician's salary. But she believes that her low overhead will allow her to exceed her previous full-time salary.

So if this is a growing trend, where are all these micropractices?

Well, you could start by looking at this website where 33 55 78 micropractices are listed. And the list is growing.

You may already have a micropractice near you. Or if not, maybe a micropractice will be starting up in your town soon. Then you'll have a choice between the new way of seeing a doctor:
  • call to make an appointment and be surprised when the doctor answers
  • get an appointment for 2PM that same day
  • barely spend any time reading the magazines in the empty waiting room as you are directed to the exam room
  • talk to the doctor who sits down and looks you in the eye and actually listens
  • spend enough time to make sure everything gets brought up and even some things that you had forgotten about
  • receive a thorough physical examination
  • leave with all questions answered with an appropriate follow up date (if any is needed)
  • since it's only 2:30PM you have time to go to the bank/post office/whatever

Or the current way of seeing a doctor:
  • call for an appointment and wait on hold
  • get an appointment for 2PM a week from now
  • wait in crowded waiting room with sick people
  • finally get called 30 minutes after the appointment time
  • wait another 10 minutes for the doctor in the cold exam room
  • spend 5 minutes with doctor who is busy looking through your chart or writing notes while you talk for 22 seconds before being interrupted
  • received a rushed and abbreviated physical examination
  • be left with unanswered questions because the doctor is late for his next patient
  • spend another 10 minutes trying to reschedule another appointment because there wasn't enough time to talk about everything you wanted
  • lather, rinse, repeat

Then we'll see who the crazy ones really are.

Friday, July 28, 2006

Untold Stories of an FP

The small town where I practice is a favorite place for the nearby entertainment industry to look for locations to shoot various movies and commercials. It's a lot cheaper to film in a pre-existing Craftsman style period house than to construct it on a set, for example. Still, I was surprised to get a call from a location manager looking for a doctor's office to use to film a Nexium commercial. She had gotten my name from the city's film liaison who knows me. (You know filming is big business when your city has a film liaison.)

Sadly, I had to explain that my office was really very small and probably not what they were looking for. She agreed saying how there'd be about 50 (!) people running around for the commercial shoot. So I gave her the name of another local doctor who has a larger office. Hopefully he'll have a good story to tell me.

Speaking of which, Hollywood is all about stories, some good, some not so good, some that are better left unspoken. Some of these stories come from real life, as I found out about a month ago when a producer for "Untold Stories of the ER" called me. He heard about me through this blog, and wondered if I might have any potentially interesting stories that could be suitable for his TV show.

Unfortunately, I explained, I didn't. As a family doctor, most of what I saw in the office was minor and not very exciting (except to the patients themselves) compared to the bloody life and death drama that occurred in the ERs. He agreed that wasn't quite what he was looking for, and I suggested he try contacting some other bloggers with ER experience. I was sorry I missed a chance to have my name in the credits of a TV show, but as I thought about it, I was glad NOT to have experienced very many "interesting" cases (as in the curse, "May you live in interesting times.").

Here are a few of the more memorable stories I have shared with medical students through the years:
1. During internship, there was a guy (whom I'll call Joe) with Munchausen syndrome who went from ER to ER complaining of a heart attack. As residents who rotated through the ER, we all saw Joe eventually at least once. Through the years, Joe had had every single cardiology test they could think of, including angiograms, and they were all outrageously normal. The worst part about it was he wasn't paying for any of it. Joe had no insurance, but the county hospital was required to treat him regardless of his financial status. And his tab was so high that there was no realistic chance of ever collecting a penny from him.

Dr. Raphael, our hospital's cardiologist, was fed up with this guy. He printed Joe's name and photo on a flyer and posted them in every local ER with a brief summary of his history. But even that didn't stop Joe, as no one had the guts to rule him out for an MI without giving him some morphine and running some kind of test. In those days, we didn't have troponin levels so it could take 3 days to rule someone out for an MI. Finally, Dr. Raphael told all the ERs to call him personally the next time Joe showed up. Sure enough, late one night Joe presented at a local hospital ER complaining of his usual crushing chest pain. Dr. Raphael quickly jumped out of bed, drove over and greeted the man. "Hiya Joe. Remember me?" Joe got a quick evaluation, then was quickly discharged by Dr. Raphael as having non-cardiac chest pain. A few days later, he tried a different ER. But who should show up again but his pal, Dr. Raphael. This time, Joe took one look at Dr. Raphael and without a word, stood up from the wheelchair and walked out of the ER. He was never seen in any of the local ERs again, but we knew that he was still out there somewhere complaining of a heart attack that wasn't real.

2. Donor kidneys have always been in short supply and usually given selectively to those who seem to have the best chance of a successful transplantation. Which is why I and my supervising resident were so surprised that Sam had gotten one. Sam was a schizophrenic who had trouble taking his antipsychotics, much less the immunosuppressants that would help prevent organ rejection. By the time Sam got to us this time, he was nuttier than a fruitcake and a danger to himself. He was incoherent and behaving irrationally, so for his safefy he was secured to his bed with a leather arm restraint. We had to get him back on his meds and wait for him to calm down.

One night, my resident and I were making the evening rounds and we looked in on Sam. He had a big goofy grin on his face as we asked how he was doing. "Aw, man, I'm feeling great. Everything's great," he said. "The doctors are great. The nurses are great. The food is great. Even the beer is great." Beer? We looked at each other. He hadn't had any visitors that we knew of. "Where did you get the beer?" we asked. "I don't know. It was just there. Kinda warm, though." Uh oh. "Was this beer kind of yellow and in a plastic container hanging off your bed?" "What? I don't know. I guess so." We looked at his empty urinal container hanging on his bedrail. No wonder his creatinine levels were so high. Sam managed to get better and was eventually discharged. But to this day, I don't drank beer.

3. Esther had was an older woman with diabetes, multiple heart attacks, and respiratory failure to the point that she was on a ventilator machine to help her breathe. She was swollen everywhere like a balloon from her congestive heart failure. She couldn't talk, couldn't eat, but she was awake although how much she was aware of we couldn't say. She had been in the ICU for 6 months, and despite many attempts at weaning her off the ventilator, she was not strong enough to support her own breathing. She was stuck in limbo. She had 2 children, a daughter who lived nearby and visited regularly and a son who lived in another state. After a while, the attending physicians felt that her situation was hopeless. It was left up to us, the residents, to try to secure an okay from her family to withdraw the ventilator so as not to needlessly prolong her suffering. Otherwise, she could continue in her miserable state for who knew how long.

Her daughter, who saw her mother's suffering in person, readily gave her OK. But her son, who never visited her, adamantly refused and wanted us to continue to do everything we could for her. When it was my turn to rotate in the ICU, I also tried to convince the son that keeping her alive like this was not a good quality of life, that turning off the ventilator was not killing her but allowing nature to take its course. On the other end of the phone, he steadfastly refused. After another month, I handed off my ICU duties to Dr. Kuartei (now Director of Public Health for the island nation of Palau). He decided to play hardball. He told the son that he was going to call him every day and give him an update on how his mother was doing. And he did just that, adding in various descriptions/opinions of how much she was suffering day after day. After 8 days of this, the son changed his mind and gave his consent to pull the ventilator. Surprisingly, Esther continued to breathe on her own off the machine, though with a lot of oxygen supplementation. She lasted for about a week before she passed, her suffering finally over. Modern medicine can be a wonderful thing, but it cannot substitute quantity of life for quality of life.

Those of some of the stories that I remember from my residency training days. If you want to share your interesting ER medical experiences with Untold Stories of the ER, they want your untold story. Who knows? Your spleen (or other body organ) might become a star.

Monday, June 12, 2006

Closing My Practice (to new patients)

Although I haven't posted in a while, I am still in business. In fact, I've had to close my practice to new patients for the past 2 months because I am having trouble keeping up with the amount of administrative work. I started my solo-solo practice about 2 years ago as an experiment to see if I could create a low overhead, low volume practice that maximized patient contact time. If I could keep my expenses down, the thinking was that I wouldn't need to see 20+ patients/day in order to survive.

The experiment is over for me. While there are energetic doctors out there who have the discipline and fortitude to keep up with medical billing and other administrative tasks, while also taking care of patients and chart documentation, I've learned that I'm not one of them. I think a practice like this (solo physician, no employees) could succeed in the right environment. This is very doable for a part-time or a cash-only practice.

Medical billing by itself is not hard. 90-95% of the time the electronically-filed claims get paid without a hitch. But the 5-10% of claims that get rejected take more time and energy than I have. Last week I waited on hold 30 minutes to speak to a Pacificare agent to ask why a claim was denied. She said they were waiting for a certificate from the patient because of a "pre-existing condition". Of course, when I called the patient, he didn't know anything about any certificate and said he would call Pacificare back. I will call again next week if I don't hear anything. But I don't have time to do this kind of chasing down unpaid claims.

So I plan to hire someone in the next few months to help part-time with billing. I am not ready to go to a cash-only model, or start charging a retainer or administrative fee, although I haven't ruled them out yet. Let's see if my fledgling practice can grow up a little so that I do less administration and more patient care. Hopefully then I can start adding new patients again.

Saturday, May 06, 2006

Gordon Moore Podcast


For those of you who are auditory learners, here is an interview with Dr. Gordon Moore from The Journal of Medical Practice Management.

Gordon Moore is a Rochester-based family physician who pioneered a low overhead, low volume practice model as an alternative to the current medical practice model. An excerpt:

Kent Bottles, MD: Do you think that you're just different than most family physicians in that you like change or that you're more willing to adapt to change?

Gordon Moore, MD: Well, maybe to some extent. You're put me a little on the early adopter spectrum of Everett Roger's Diffusion of Innovation Curve. But I think that's true in a lot of us. There's some aspect in each of our lives where we can see ourselves as early adopters and there are parts of my life where I'm clearly a traditionalist or a laggard. And so I think if we as individuals can tap into that early adopter or early majority part, we can get on the bandwagon and start to effect real and lasting change.

On the other hand, I think they'd be somewhat motivated just by the plain misery of the way things stand currently. It's not a lot of fun out there. I've talked to lots of audiences across the country where the only thing they look forward to is getting a paycheck. And I'm pretty certain that not that many people got into healthcare just for the paycheck. I'm sure it's nice but I think that most people who become physicians have some sense of mission, wanting to help reduce suffering and improve health. And that's a very noble mission that I think has gotten lost because of the fee of finance and overhead and all these other things that have obscured what it is we're really after.

Kent Bottles, MD: Well it sure seems to me as I talk to physicians that many of us are not that happy with what we're doing and I take my hat off to you for at least trying to make your life more interesting and more enjoyable, and make your patients have a better relationship with you.

Sunday, April 02, 2006

The Bigger Picture

I am on vacation and enjoying the final chapter of the story known as March Madness, and my alma mater is once again reaching for that National Championship in basketball. It has been a wild but exciting ride, with the Championship game to be played tomorrow night against the Florida Gators. As remarkable as this basketball season has been for UCLA, some things stand out a little more, such as when UCLA overcame a 17 point deficit to defeat Gonzaga. While the comeback was one for the ages, what happened after the game was just as memorable. Adam Morrison, Gonzaga's star player and future NBA draft pick, had crumpled to the floor in disappointment and tears after his team's defeat.
UCLA's Arron Afflalo and Ryan Hollins, in the middle of celebrating their come-from-behind win, went over to Morrison to help up the player who had caused them fits for the previous two hours. The gesture wasn't lost on Morrison.

"At first I didn't realize who it was," Morrison said. "That's just a sign of a great program and great people, as far as they're concerned.

"They had enough guts as a man in their moment of victory to pick someone up off the floor. If I could thank them I would. That's a sign of great people and great players. That's more than basketball."

As the legendary former UCLA basketball coach, John Wooden, used to say, "What you are as a person is far more important that what you are as a basketball player."

-----------

When I used to work at Kaiser I had medical students shadow me, and one day one of them asked me why I was always so persistent in trying to get patients to stop smoking. Did I have a relative who died because of smoking, he asked. No, I didn't. In fact, few of my friends or relatives smoked. But I have known many smokers and ex-smokers through my medical career and have seen what smoking can do to them. I explained to the student that the patient's cold or back pain would be gone within a week no matter what we did. Oftentimes what we did as doctors, the prescriptions we wrote, the tests we ran, wouldn't change a patient's life at all. But if we could get someone to quit smoking, then that could save their life someday. That was the bigger picture.

That is why I was happy to receive this e-mail from a patient recently:
I wanted to send you an email to follow-up with you. I'd like to sincerely thank you for your advice regarding the diagnosis of my shingles and it being caused by stress factors in my life. Immediately following my appointment with you, my husband and I sat down and had a long discussion about our priorities and causes of stress. We decided that the majority of the stress in our lives was from the pressures of owning our home in our current financial position. We decided it was unwise and unhealthy to continue on that path...the health costs were simply not worth it!

After prioritizing our lives, we decided to put the home on the market and live in subsidized graduate student family housing at my husband's university. He also accepted a new position there which had him doing an extensive commute which meant he was rarely home...also adding to the stress factors.

Anyway, I just wanted to follow up with you and sincerely thank you for the time you spent talking with me about the causes of my shingles and how to takes steps to get myself healthy, including minimizing stress factors in my life. I sincerely appreciate your care. You will be glad to know that the symptoms are healing, though I still have numbness. I do feel these are slowly getting better, though.

This person's shingles probably would have resolved with or without my intervention. But her stress was affecting her health and eventually might have led to worse things, such as headaches, depression, obesity (due to stress-induced overeating), cancer (due to a depressed immune system). I'd like to think that I helped her see the bigger picture, and helped her get to where she wants to be. Hopefully, I can do that for others, too.

As a physician, having the time to be able to talk with people about their lives makes all the difference, and I am grateful that I have the kind of practice where I can do that. My wish is that all physicians will someday be able to have the time to do that, too, although I think we still have a long way to go before that happens.

To paraphrase Coach Wooden, "How you treat someone as a person is far more important that how you treat them as a patient."

----------

Whether or not UCLA wins their Championship game tomorrow, as Coach Wooden used to say, as long as they did their best, they are a success. This team has already demonstrated to me with their class and character that they are winners.

Go Bruins!

Saturday, March 18, 2006

Marathon

It was a challenge but I finally made it to the eve of the LA Marathon without getting a cold/flu, which I feel like I've been dodging for the past month in the office and at home. I've been feeling as if I might be coming down with something over the past 2 days, but no fever or shaking chills yet. That may change by tomorrow, though. At least the weather report says it won't rain. The last time I ran the LA Marathon it rained from start to finish, but I finished anyways. I've always finished every marathon I've ever started, but I am not a very fast runner. In fact I usually run the first half, then run-walk-hobble the second half. But once you've finished one, you tell yourself, "I can do this."

That's kind of how I feel my solo practice is turning out to be, a marathon. I started strong and enthusiastic, but now I'm way out there in the middle of the course. I'm a long long way from the start and the end is not in sight. I don't have the same energy I had at the outset. My fingers tend to cramp up more from typing such long progress notes (one of the drawbacks of EMRs is limitless space to write). I struggle to catch up with billing and rebilling and chasing down denied claims. Unlike tomorrow's marathon, though, this race won't be over after tomorrow. But just as I will do tomorrow morning (after I make a 6AM home visit to repack an elderly patient's I&D wound), I will just keep plodding along until I reach my goal.

By the way, how much further do I have to go anyways? That far?

Oh, man. I need some glucose.