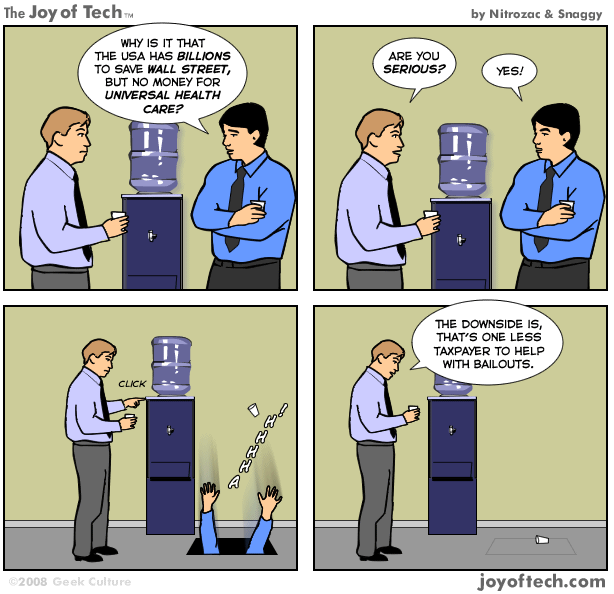
Via joyoftech.com
For years now, they’ve told us that we can’t afford—that the government providing healthcare to all people is just unimaginable; it can’t be done. We don’t have the money to rebuild our infrastructure. We don’t have the money to wipe out poverty. We can’t do it. But all of a sudden, yeah, we do have $700 billion for a bailout of Wall Street.It's rather sickening.

Imagine going to your favorite restaurant. You are greeted at the door by the hostess, who seats you and takes your drink order. You order through your favorite waiter, Andrew, who recommends the special of the day: prime rib with a dinner salad and a chocolate tort for dessert. Soon after, the food is brought out and it is delicious. You have time to enjoy your food. You then receive the bill and pay for your meal, returning to your home satisfied, all your dining needs met. Let’s say you paid $75 for this meal:$50 for the steak, $10 for the salad and $15 for the dessert.
A change then occurs in the restaurant industry. A new form of eating out has been adopted. Your favorite restaurant has now contracted with over 30 different ”restaurant insurance companies.”
Anticipating another pleasant dining experience, your return to the restaurant with your new “subscribers card.” You pay your $5 “copay” and sit down in the foyer of the restaurant. After waiting an hour, even though you made reservations, a harried Andrew greets you and quickly takes your order after you briefly glance at the menu. The food arrives at your table, but before you have time to truly enjoy it, Andrew informs you that “your time is up” and the table is reserved for another party. You are escorted outside with your hastily boxed left-overs.
What has happened to the restaurant? Behind the scenes, the restaurant owner has learned some tough realities of the “new system.” During the first month of taking insurance, the owner submits the charges for the $75 steak dinner. The contract with this particular insurance company already states that they will only pay $45 for the $50 steak, but the owner decides that the extra customers brought to the restaurant by contracting with this insurance company will more than off-set this small loss.
The first attempt at collecting the $75 dollars for the full meal is returned unpaid due to a clerical error. The owner mistakenly used the number assigned by another insurance company. The owner mails the corrected form.
In response to the second request for payment, the insurance company does not send a check, but a detailed questionnaire: Was basil used in seasoning the steak? Was it necessary to use basil for this particular recipe? Did the restaurant ask for permission to use basil from the insurance company before serving the steak? The owner submits the answers, emphasizing that the basil is part of a family recipe that made the restaurant famous.
The owner waits another week (it has now been 3 weeks since the dinner was served). The check arrives three and a half weeks after the meal was served. The check is for $20 and states that it is specifically for the steak. The check also comes with a letter stating that no billing of the patron may occur for the salad, but no other explanation is enclosed. No mention is made of the $15 dessert.
The now frustrated restaurant owner calls the provider service number listed in the contract. After five separate phone calls to five different numbers (The harried voice behind phone call number four explains that the insurance company has merged with another insurance company and the phone numbers had all changed last week, sorry for the inconvenience…), the owner gets to ask why, when the contract says the steak will be paid at $45, has the check only been written for $20? And what happened to the payment for the salad and the dessert?
As it turns out, this particular patron’s insurance contract only pays $45 when the patron has reached their deductible, which this patron has not at this time. The remaining portion of the steak must now be billed by the restaurant to the patron directly.
The $10 for the salad would have been paid if the patron had ordered it on a different day, but, per page 35 in the contract, because it was billed on the same day as the steak, it is considered to be part of the payment for the steak and no extra money can be collected from the patron or the insurance company.
The dessert should have had a “modifier” number put with its particular billing code in order to receive payment when billed with the steak and the salad.
Realizing that the billing is quite a bit harder than anticipated, the restaurant owner hires a person to specifically make sure these errors do not occur again. The owner must lay off the hostess and the bus boy to hire the biller, but feels these duties can be added to the waiter’s other responsibilities.
In the meantime, the restaurant owner has now had to have the waiter take on the job of answering the phones due to the now high volume of phone calls from patrons questioning why they are receiving bills for meals they ate over 2 months ago and why did their insurance company not pay for this portion of the meal. This extra work is now resulting in longer times patrons must wait to be seated and served, and grumblings from the waiters who “were not hired or trained to do this kind of work.”
The owner now realizes that, although the dinner originally cost $75 to make, only $22 has been paid. The remaining $30 billed to the patron has now cost $10 in overtime for the biller and mailing a second bill to the patron after the first bill went unpaid. By the third billing cycle, the owner realizes a collection agency must be employed in order to have any hope of receiving any portion of payment from the patron.
In order to meet costs, the restaurant owner now must seat twice as many patrons in the same amount of time. The owner has now over-extended the waiter, who was an excellent waiter, but is now taking on the roles of host, phone answering and table bussing, as the pay for these employees has been shifted to the biller and the collection agency.
What was once an outstanding business that focused on fine dining and customer service has now been turned into a business in the business of trying to get paid.
Alas, I wish this were a fictional tale, but it is not. The only fictional portion is that this is not your favorite restaurant, but your favorite doctor’s office, who is responsible not for meeting your dining needs, but those of your health.
Megan Lewis, M.D.
A family doctor in rural Colorado.
Imagine one morning you're craving something sweet, so you stop by the corner doughnut shop. Turns out the wait is half an hour, the clerk is rude and, when you finally get it, the doughnut is stale. Would you buy doughnuts there again? Of course not.Because not enough people are pissed off enough with the current system to demand a change - yet.
Yet, every day, millions of Americans put up with just that kind of service in their physicians' offices. And they keep going back.
Anyone who has visited a primary care doctor lately knows the drill: You show up on time, only to wait 45 minutes or even an hour. In the examination room, the physician (who offers no apology) seems distracted, harried and eager to get to the next patient. Then you're referred to a specialist -- who doesn't have an opening for a month.
Every politician and his Aunt Martha has a scheme to overhaul American healthcare. But not one of them will solve this problem: Most doctors are awful at serving their patients. The typical hair salon pays more attention to customer service than the typical doctor.
Why?
When was the last time that your family physician made a house call? Or you were able to make a same-day appointment, see the doctor without waiting -- and then spend a half hour talking over your treatment plan?
These seemingly old-fashioned images are at the core of practicing medicine for Dr. John Brady of The Village Doctor. Working and living in the Hilton Village area of Newport News, Brady and nurse Jeannie Arado provide preventative care, management of chronic illnesses and special care coordination for nearly 1,500 patients.
As he developed his business model, Dr. Brady became active in a national movement known as the "Ideal Medical Practices, " or "IMP," which focuses on managing practice work-flow and communications to increase quality in primary care. Brady's efforts and those of other IMP practices around the country, gained national attention in 2006, with an article in The Wall Street Journal.
For his accomplishments, Brady was recently selected by the Virginia Academy of Family Physicians as the 2008-2009 Virginia Family Physician of the Year. This statewide award, which is the academy's highest honor, is presented to "a family physician who gives compassionate care, is active in the community, and serves as a role model to medical students and other medical professionals."
Dr. Jean Antonucci says a physician can learn a lot by meeting a patient in the waiting room. She notes how difficult it is for the patient to get out of the chair, how easily he walks, whether his speech is slurred and whether his mind is confused.
Antonucci, a family practitioner in Farmington, does these waiting-room observations every workday.
She has no staff, practices out of one room, performs duties typically handled by a nurse or medical assistant and offers patients a $10 discount for handling their own insurance claims. She also has fewer appointments a day than most of her peers and is available to her patients around-the-clock.
Antonucci says she's never had such a good time practicing in her 21-year career as a doctor.
"It's not only good care for patients. It's just joyful to do it," said Antonucci, who opened her current practice three years ago.
Antonucci is among a small but growing number of doctors who are radically paring down their practices. They reason that if their overhead costs are lower, they can get by with fewer patients.
Dr. Karen Hover opened a new cash-based solo practice in Bangor in July. She uses a menu of services with set fees that charge $50, for example, for a single-issue visit and $100 for a full physical.
"It's supposed to be really simple. They can look at it and decide what they want," Hover said. "That's our contract for the visit. I don't go over that and they don't go over that."
Hover said she was troubled that the uninsured pay more for the same services than insurance companies. Insurers negotiate discounts but individuals are at a disadvantage, she said.
Because billing requires a lot of staff resources, cash payments allow her to cut her expenses. She employs only a receptionist.
As a family doctor, I am reminded daily that American health care is broken. A local administrative assistant, "Jane," was working on her roof on a Wednesday afternoon when she fell. X-rays showed two elbow fractures. She was put in splints that immobilized her arms from the armpits to the fingers. She went home at midnight in the care of a friend with instructions to call her doctor in the morning for home services.
Nobody considered that home services are structured to provide only a few hours of support a day. She recalled: "I couldn’t scratch my nose, or feed myself, or get a glass of water, or pull my pants down." She needed around the clock care. Jane called her insurance company, which told her that her plan included 100 days of skilled care.
Arrangements were made to go to a rehabilitation facility on Friday, which was good because Jane’s friend had to go back to work. When Jane arrived, around noon, administrators told her that the insurance company had denied her claim and that she could not be admitted because she had no need for skilled medical care. After a couple of hours on the telephone, no one had a better idea, so she was sent back to the emergency room. By this time, she needed to go to the toilet, but staff refused to take her because of fear of liability. Her ex-husband helped her.
The waiting room of Ramona Seidel's family medicine practice is empty, and she works hard to keep it that way.
After several years in a traditional suburban group practice that blended pediatrics and family medicine, Seidel quit to start her own micro-practice in Annapolis: a low-overhead, high-tech office that gives her more control over how she treats patients and more time to spend with them. She's happier. Her patients are happier. And she's pretty convinced they are healthier having a physician who knows them well.
Are you sure you want to call youself "IMP" ? The word imp has a negative connotation in its definition.

 Posts
All Comments


